





When should you get a flu shot in 2026? For most people in the United States who need one dose, September and October are good months to receive the 2026–27 seasonal influenza vaccine, ideally by the end of October. Vaccination remains recommended later while flu viruses circulate. The CDC recommends annual vaccination for everyone age 6 months and older, with rare exceptions. Some young children need two doses at least four weeks apart, and adults 65 and older have preferred vaccine options.
This guide explains the current US recommendations, what changed in the 2026–27 formulation, and how to plan an appointment. It draws on the CDC’s 2026–27 season page and its interim clinical considerations, both updated in September 2026. It is general information, not an individual assessment; a clinician can advise on allergies, past reactions, pregnancy, immune conditions, and a child’s dosing history.
The short answer: September or October for most people
CDC guidance says most people who need only one flu vaccine dose should ideally be vaccinated during September or October. The aim is to be protected before influenza becomes widespread while avoiding an unnecessarily early vaccination for people whose protection may wane later in the season. Antibodies generally take about two weeks to develop after vaccination, so a shot on the day of a trip or family gathering does not instantly protect you.
If October passes and you are still unvaccinated, do not assume the opportunity is gone. The CDC recommends continuing vaccination after October and throughout the season as long as flu viruses are circulating and unexpired vaccine is available. Influenza activity differs each year and across regions; no single calendar date can guarantee that exposure will begin only afterward.
For most adults, especially those 65 and older, vaccination in July or August is generally discouraged because protection can decline over a long season. An early dose can be reasonable if there is a concern the person will not be able to return later. Timing differs for some children and pregnant patients, discussed below. If your appointment options are limited, speak with your healthcare professional rather than skipping vaccination entirely.
What is new about the 2026–27 flu vaccine?
The US 2026–27 vaccines are trivalent: they target three influenza virus components, two influenza A components and one influenza B/Victoria component. The CDC says the FDA recommended updating all three components compared with the 2025–26 vaccines, including an H3N2 update intended to address the subclade K virus that spread widely in the prior season.
That is a reason to seek the current-season vaccine even if you received last season’s shot. The viruses change, vaccine composition is reviewed annually, and immune protection from previous vaccination declines over time. The exact match between the selected vaccine components and viruses circulating months later cannot be known with certainty at the start of the season.
Vaccination reduces the risk of flu and serious outcomes but is not a promise that you cannot become infected. A person can be exposed before protection develops, encounter a different strain, or still become ill despite vaccination. CDC notes that vaccinated people who get flu may nonetheless have less severe illness. Do not treat an early estimate from a previous season as a guaranteed effectiveness percentage for 2026–27.
Who should get vaccinated?
The CDC’s broad recommendation is for people 6 months of age and older in the United States to receive a seasonal flu vaccine, with rare exceptions. The exact product must be approved and appropriate for the recipient’s age and health status. Babies younger than six months are too young for a flu vaccine, which makes prevention among parents, caregivers, and other close contacts especially relevant.
Vaccination is particularly important for people at higher risk of serious complications. The CDC’s clinical guidance identifies young children, older adults, pregnant people, and people with several chronic conditions or compromised immunity. This includes, for example, people with asthma or diabetes, though individual medical circumstances vary. Household members and caregivers of higher-risk people should also pay attention to annual vaccination.
Do not decide that a healthy person “doesn’t need” a shot solely because they are unlikely to be hospitalized. The annual recommendation covers people beyond the highest-risk groups. Conversely, someone with a severe reaction to a previous flu vaccine or another specific contraindication needs a clinical conversation before choosing a product. General rules cannot substitute for that history.
Children: when are two doses needed?
Most people age nine and older receive one dose for the season. Some children ages 6 months through 8 years require two doses at least four weeks apart. The decision depends on the child’s previous flu-vaccine doses and whether the history is known. According to the CDC’s 2026–27 clinical considerations, a child in this age range who has not previously received at least two appropriately spaced doses before the season’s cutoff, or whose history is unknown, requires two current-season doses.
If your child may need two, contact the pediatrician or vaccination provider early. The CDC says the first dose can be given as soon as vaccine becomes available so the second can ideally be completed by the end of October. A family that waits until late October for the first dose cannot give the second only a few days later; the spacing matters.
Bring or locate the child’s vaccination record and ask the provider to apply the current dosing algorithm. Do not infer the schedule from age alone. For a child who requires only one dose, CDC says July or August vaccination can also be considered. A pediatrician can advise on the practical timing for your family.
Adults 65 and older: preferred options
For adults 65 and older, CDC preferentially recommends one of three types over standard-dose, unadjuvanted vaccine: high-dose inactivated, recombinant, or adjuvanted inactivated influenza vaccine. The CDC says the evidence suggests these options may provide better protection in this age group. It does not give a universal ranking among the three.
If none of the preferred options is available at an opportunity to be vaccinated, the CDC advises getting another age-appropriate flu vaccine rather than missing the chance altogether. Call a pharmacy or clinic to check stock if you are arranging a shot for an older family member. Ask for the vaccine name and make sure the provider knows the patient’s age and medical history.
A 65-year-old who received a complete seasonal vaccination early should not assume a second dose is recommended later. The CDC’s clinical guidance says revaccination as a seasonal booster is not recommended for people fully vaccinated for that season, regardless of when the dose was given. Ask a healthcare professional if there is uncertainty about what was administered.
Pregnancy and the flu shot
The CDC recommends flu vaccination during pregnancy and says an inactivated or recombinant vaccine may be given in any trimester. Its clinical guidance advises against the live attenuated nasal-spray vaccine during pregnancy. A healthcare professional can help identify a suitable product and schedule it with other prenatal care.
For someone in the first or second trimester during July or August, September or October is generally preferable unless later vaccination may not be possible. Vaccination during July or August can be considered for a person already in the third trimester because it may help protect their baby in the first months after birth, when the infant is too young to be vaccinated. These are timing considerations, not a reason to miss an accessible appointment without consulting a clinician.
CDC notes that vaccination during pregnancy is associated with reduced flu illness among pregnant and postpartum people and their infants. Bring up previous vaccine reactions, medications, and any questions about timing with the prenatal care team. The specific vaccine matters: a nasal spray and an injectable shot are not interchangeable in pregnancy.
What about the nasal-spray vaccine?
The live attenuated nasal-spray vaccine is approved for certain people ages 2 through 49. It is not appropriate for everyone in that range. The CDC says it should not be used during pregnancy or in immunocompromised people, and other medical conditions can also make it unsuitable. Check with a provider before choosing it simply because it avoids a needle.
An age-appropriate injectable vaccine is available for many people who cannot use the nasal spray. For most people younger than 65, the CDC does not prefer one licensed age-appropriate flu vaccine over another, subject to the recipient’s health and specific exceptions. Product approvals and recommendations should be checked for the 2026–27 season rather than inferred from an old brand list.
Egg allergy, previous reactions, and other precautions
Having an egg allergy alone does not automatically rule out flu vaccination. The CDC says people at least six months old with egg allergy may receive any otherwise appropriate influenza vaccine, including egg-based products, without extra precautions solely because of the egg allergy beyond those used for vaccination generally.
A severe allergic reaction to a previous flu vaccine or one of its components other than egg is a different issue and may contraindicate a particular product. A history of Guillain-Barré syndrome within six weeks after a prior flu vaccine is a precaution requiring individualized assessment. These details are reasons to tell the vaccination provider your history before the appointment.
A minor cold may not necessarily prevent vaccination, but a more serious current illness can affect timing. If you are unwell or have had a complicated vaccine reaction, call the clinic for advice. Do not use a general article to self-select a product or override a clinician’s assessment of risk and benefits.
Where can you get a flu shot in the US?
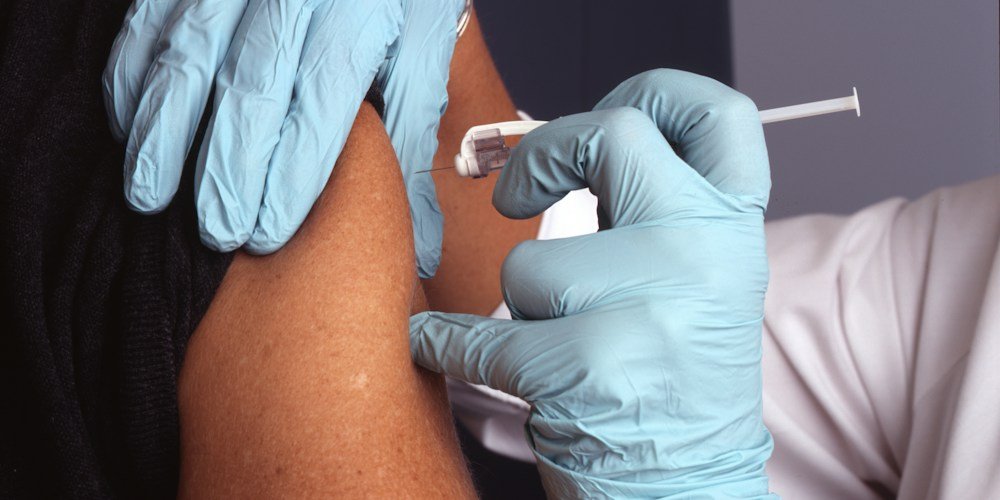
CDC lists doctors’ offices, clinics, local health departments, pharmacies, urgent care centers, college health centers, and some schools and workplaces as potential vaccination locations. Availability and age rules vary by provider and state. Before visiting, confirm that the location has a current 2026–27 vaccine, serves your age group, and accepts your insurance if you intend to use it.
Check what the appointment will cost under your particular plan or program. Coverage and network rules can differ, and we are not promising a zero-dollar visit for every reader. If you have no regular doctor, a local health department can help you identify options. For a child who needs two doses, ask whether the site can schedule both appointments.
Keep a record of the date and product you receive. Parents should preserve children’s dose history because it can affect the next season’s scheduling. If you are traveling, CDC’s clinical guidance suggests considering vaccination preferably at least two weeks before departure when protection is needed for a trip, while taking account of the season and your risk.
What side effects can you expect?
A flu shot cannot give you influenza. Inactivated shots use killed virus, and recombinant vaccines use selected proteins. The CDC says common effects after a shot can include soreness, redness or swelling at the injection site, headache, fever, muscle aches, nausea, or fatigue. These effects are generally mild and short-lived compared with influenza illness.
Nasal-spray side effects can include a runny nose and other mild symptoms, depending on age. A severe allergic reaction is rare but requires urgent medical attention. The CDC also notes a possible small increased risk of Guillain-Barré syndrome after flu vaccination; anyone with a relevant history should discuss the recommendation with a clinician rather than deciding from a headline.
If you develop flu-like symptoms soon after a shot, that does not mean the shot caused influenza. You may have been exposed before vaccination or during the roughly two-week period before protection develops, or have another respiratory illness. Seek medical advice when symptoms are severe, you are at higher risk, or you are worried.
If you get sick despite vaccination
Flu vaccination is one layer of prevention, not a replacement for medical care. If you develop symptoms and are in a higher-risk group, contact a healthcare provider promptly. The CDC advises seeking emergency care for emergency warning signs and reaching out to a provider when you are very sick or concerned. A clinician may consider testing or treatment based on your circumstances.
Flu, COVID-19, and other respiratory infections can share symptoms. Do not assume that a fever and cough are definitely influenza or that vaccination makes every flu-like illness harmless. Follow local public-health guidance, stay home when sick, and use appropriate steps to avoid exposing others.
Common questions about the 2026 flu shot
Is September too early?
For most people who need one dose, no. CDC identifies September and October as the ideal period. Its caution about getting vaccinated too early generally concerns July and August for most adults, particularly older adults. Individual access or travel considerations can change timing.
Is November too late?
No. Vaccination is recommended after October while influenza viruses circulate and vaccine is available. It is better to check a local appointment than to abandon the season because you missed a preferred month.
Do I need a new shot if I got one last winter?
Yes, the CDC recommends vaccination every season for eligible people. The 2026–27 vaccine composition differs from 2025–26, and protection can decline over time. Ask your provider if your prior dose was actually from the current season or if your record is unclear.
Does the flu shot work immediately?
No. The immune response takes about two weeks to develop. Continue other sensible prevention measures and avoid assuming you are protected on the day of vaccination.
Should I ask for a high-dose shot if I am younger than 65?
Do not choose based on the label alone. CDC’s usual preference for high-dose, recombinant, or adjuvanted options applies to adults 65 and older. There is a specific exception for some solid-organ transplant recipients ages 18 through 64 who take immunosuppressive medicines. Your clinician should determine which product is appropriate.
Make a simple vaccination plan
Check your household’s ages and vaccination records, particularly for children under nine. Look for a current-season appointment in September or October; ask about a second pediatric dose if relevant. Tell the provider about pregnancy, immune conditions, prior severe reactions, or a history of Guillain-Barré syndrome. If you are 65 or older, ask which preferred option is available. Keep the record afterward and consult the CDC for updates as the season progresses. For more evidence-based wellness coverage, browse our Health section.
Sources and review date: CDC 2026–27 flu season, CDC interim clinical considerations, and CDC key vaccine facts, checked September 24, 2026. This article provides general US public-health information. A qualified healthcare professional can address individual eligibility, contraindications, and timing.
Other Articles

Amazon Prime Big Deal Days 2026: Dates, Deals and How to Shop Smart
Apple TV 4K vs Roku Ultra (2026): Which Streaming Device Should You Buy?




No Comment! Be the first one.